Clinical Trials
April 28, 2026

Definitive Guide: How to Automate Clinical Trial Accruals


Key takeaways

Introduction: Why Clinical Trial Accrual Automation Is No Longer Optional

For biopharma finance teams, clinical trial accruals take a lot of time. They are also prone to errors during the R&D close. Analysts spend days chasing CRO invoices. They manually reconcile spreadsheets and build accrual estimates. Those estimates are outdated the moment they are finished. At the end of the month, the team is exhausted and the numbers are still wrong.

The good news is this does not have to be the norm. Automating clinical trial accruals is now within reach for biopharma companies of all sizes — and the results are measurable. Teams that have made the shift report up to a 75% efficiency gain, a 60% faster close cycle, and forecast accuracy that exceeds 90%.

This guide explains what clinical trial accrual automation means. It explains why this challenge is especially difficult in biopharma R&D. It also shows how to approach it step by step. It explains what to look for in a purpose-built solution.

What Are Clinical Trial Accruals?

A clinical trial accrual is the process of recording R&D expenses in the correct accounting period. It applies even if invoices arrive later. Under GAAP and IFRS, biopharma companies must record costs as providers perform the services, not when providers bill them.

In practice, this means estimating how much work a CRO, clinical site, or other vendor finished by each period end. This applies even if no invoice has arrived. The accrual bridges the gap between operational progress and the general ledger.

Clinical trial accruals typically cover:

  • CRO pass-through and service fees based on milestone completion and percent-complete estimates
  • Investigator fees and site costs tied to patient enrollment and visit activity
  • Central lab, imaging, and ancillary vendor costs based on sample volumes and service delivery
  • Change orders and protocol amendments that alter original contract values
  • Foreign exchange adjustments for multi-currency global studies

Each of these streams requires different data sources, different calculation logic, and different sign-off workflows. Across a portfolio of five or ten active trials, the complexity compounds quickly.

Why Manual Accrual Processes Break Down in Biopharma

Most biopharma finance teams still use ERP systems (SAP, Oracle, NetSuite), Excel files, and email to manage clinical accruals. This approach creates four structural problems that no amount of spreadsheet optimization can solve.

1. Lack of Real-Time Visibility

Accruals calculated from delayed CRO invoices or month-end confirmations are always looking backward. By the time estimates are final, study activity may have shifted. Enrollment may speed up, a site may drop out, or a protocol amendment may change scope. The accrual goes stale before you post it.

2. High Dependency on Manual Processes

Building an accrual model in Excel requires analysts to pull data from many systems. These can include EDC platforms, IRT systems, procurement tools, and contract management systems.

Analysts then copy the data into a workbook, apply formulas, and reconcile results with prior periods. Each handoff introduces the risk of error. Each formula cell is a potential failure point that auditors will want explained.

3. Disconnected Systems and Siloed Data

No single system connects operational trial progress to financial impact. Clinical operations teams track enrollment in one platform; finance tracks budget vs. actuals in another. When a change order is approved, the accrual model does not update automatically.

When a site is activated, the accrual model does not update automatically. Finance hears about it at month-end — if they hear about it at all.

4. Forecast Inaccuracy and Budget Overruns

Static accrual models assume the world stays constant between updates. In clinical development, it never does. Without dynamic, scenario-aware models, finance teams can't accurately project trial spend — and programs run over budget without warning.

"Condor is like night & day from our previous models." — Trishula Therapeutics

The Anatomy of a Modern Clinical Trial Accrual Process

Before you can automate the process, it helps to understand what a well-designed accrual workflow actually looks like. The architecture has three distinct layers.

Layer 1: Data Ingestion

The inputs to any clinical accrual include:

  • Contract data — CRO agreements, CTAs, site contracts, and all associated change orders
  • Operational assumptions — enrollment timelines, site activation status, percent-complete by service line, and visit completion rates
  • Live operational data — EDC data (grant activity), IRT data (site-level enrollment), ERP transaction data, and procurement system records

In a manual process, analysts gather this data by hand. In an automated process, integrations pull this data continuously and map it to the right contract line items.

Layer 2: Calculation and Processing

With the right data, the system uses calculation logic to create accrual estimates for every vendor and service line. This includes:

  • Percent-complete calculations for CRO services
  • Investigator fee accruals based on visit activity
  • Foreign exchange gain/loss calculations for global studies
  • Amendment-in-progress reconciliations when change orders are pending

Layer 3: Outputs and Workflow

The outputs of the accrual process feed directly into the financial close. Specifically, the system produces:

  • Journal entries ready for ERP posting
  • Vendor reconciliation packages for CRO review and sign-off
  • SOX/SOC-compliant audit logs and supporting documentation
  • Dashboards showing accrual status, budget vs. actual, and trial-level spend

This is also where the guided workflow lives. It includes checklists, role-based approvals, and audit trails. These features make the close defensible to Big 4 auditors.

How to Automate Clinical Trial Accruals: A Step-by-Step Approach

Step 1: Centralize Your Contract Data

The foundation of any accrual automation effort is a unified, structured repository of all your clinical contracts and amendments. This means contract value by service line, milestones, budget categories, and all approved change orders.

Without this foundation, automation is impossible — you can't calculate percent-complete against a contract you haven't structured. Start by extracting and standardizing your CRO agreements, CTAs, and ancillary vendor contracts.

Step 2: Map Operational Data to Financial Categories

Next, create a reliable link between your study work and the records in the general ledger. This requires SMART mapping logic. It translates key milestones, like a patient visit, a lab sample, or site activation. It maps them to matching contract line items and budget categories.

This mapping is where purpose-built clinical finance software creates the most value. Generic ERP systems and accrual tools were not built for the clinical R&D data model.

They need major custom setup, or manual workarounds, to meet these needs.

Step 3: Integrate Your Data Sources

Once your contracts are structured and your mapping logic is in place, you need live data flowing into your accrual models. Integration points typically include:

  • EDC platforms (Medidata, Veeva Vault, etc.) for grant and visit data
  • IRT systems for site-level enrollment and randomization
  • ERP and procurement systems for purchase orders and invoice status
  • Contract management systems for approved change orders and amendment status

Automated data ingestion eliminates the manual copy-paste that accounts for a significant portion of close cycle time — and the majority of accrual errors.

Step 4: Automate Calculations and Reconciliations

With structured data flowing in, the system can calculate accruals programmatically. Automated calculations should cover:

  • CRO service accruals by percent-complete methodology
  • Pass-through cost accruals based on operational data
  • Investigator fee calculations by site and patient activity
  • Gain/loss calculations for foreign-denominated contracts
  • Intelligent reconciliation against prior-period estimates and invoices received

Automation here doesn't mean black-box algorithms. It means repeatable, auditable logic that finance teams can explain to auditors and sign off on confidently.

Step 5: Implement Guided Close Workflows

Automation handles the calculation. Workflow automation handles the coordination. A purpose-built clinical finance system should include:

  • A financial close checklist with task assignments and status tracking
  • Role-based approvals for accrual review and sign-off
  • Integration with accounting systems for journal entry posting
  • Audit logs that capture every change, assumption update, and approval

This is where SOX compliance gets built in rather than bolted on. Teams working toward IPO readiness or operating under external audit scrutiny will find that structured workflows reduce the risk of audit findings tied to clinical R&D accruals.

"This [financial close] would never have been possible without Condor." — Intra-Cellular Therapies

Step 6: Build Dynamic Forecasting on Top of Actuals

The final step — and the one that transforms accruals from a compliance function into a strategic tool — is connecting accrual actuals to a forward-looking forecast. When your accrual data is clean, structured, and current, you can build scenario models that project trial spend under different enrollment, amendment, and timeline assumptions.

This closes the loop between the close process and FP&A, giving CFOs and VPs of Finance the real-time visibility they need to manage R&D budgets proactively.

Key Capabilities to Look for in a Clinical Trial Accrual Automation Platform

Not all clinical finance tools are built the same. When evaluating solutions, look for these capabilities:

Purpose-built clinical data model

Generic ERP add-ons and industry-agnostic accrual tools (like Gappify or BlackLine) were not designed with biopharma R&D workflows in mind. A purpose-built platform should natively understand CRO contracts, CTAs, investigator fees, and protocol amendments — without requiring custom configuration to model these structures.

Automated data ingestion

Look for native integrations with EDC platforms, IRT systems, ERP systems, and procurement tools. Manual data imports are a bottleneck and a source of error.

SMART mapping and intelligent reconciliation

The system should automatically map operational data to contract line items, flag variances, and surface amendment-in-progress situations that require reconciliation before the close.

SOX-compliant audit trail

Every calculation, assumption change, and approval should be logged with user, timestamp, and rationale. This is non-negotiable for public companies and Series C+ stage companies preparing for audit.

Unified view for Accounting, FP&A, and Clinical

The best systems give each function a role-specific dashboard built on the same underlying data model — so there's one version of the truth, not three.

Scenario-based forecasting

The platform should allow finance teams to run "what if" models based on enrollment changes, protocol amendments, or timeline shifts — with the accrual layer feeding directly into the forecast.

The Business Case for Clinical Trial Accrual Automation

The ROI on clinical accrual automation compounds quickly. Organizations that have implemented purpose-built automation report:

  • 75% efficiency gain on the accrual process itself
  • 60% faster financial close cycle
  • 90%+ forecast accuracy versus prior-period actuals
  • 20% savings per change order through improved reconciliation
  • $200K–$10M in vendor budget savings per trial, on average

Beyond the numbers, there is a scaling benefit that spreadsheet-based processes simply cannot provide. One company scaled from 2 active trials to 10 in 120 days — without adding headcount — because their accrual process no longer required a dedicated analyst per study. Another team unlocked over $5M in clinical program savings in a single program through better vendor reconciliation and change order management.

For finance leaders, the business case is straightforward: manual accruals are a constraint on how fast the company can grow. Automation removes that constraint.

Common Objections — and How to Address Them

"We already have an ERP."

ERPs manage transactions. They were not built to calculate clinical trial accruals based on percent-complete methodologies and operational trial data. Most companies using SAP or Oracle for clinical accruals are doing the actual calculation in Excel and posting the result to the ERP. The automation opportunity is in the calculation layer, not the GL.

"Our process works fine for now."

Manual processes work until they don't.

Inflection points often come sooner than teams expect. A new CFO might join. An IPO process might start.

A Series C audit might begin. A pipeline might expand. Building automation early is far less disruptive than adding it under pressure during a close or audit.

"We don't have the IT resources for implementation."

Purpose-built clinical finance platforms support fast implementations with minimal IT burden. The heavy lifting is in the clinical data model and integration layer. It comes pre-built, not from custom development.


Conclusion: From Reactive Close to Proactive Control

Automating clinical trial accruals is not just an efficiency play. It is the foundation for transforming clinical finance from a reactive, backward-looking function into a proactive one.

Finance teams gain real-time visibility into trial spend. They also get accurate forecasts. They can scale as the pipeline grows.

Centralize your contract data. Link your key operational data sources. Move calculations out of spreadsheets and into a purpose-built system. The result is a faster close, cleaner audits, and a finance team that keeps up with complex biopharma R&D.


Condor is the Financial Cloud for Pharma R&D — purpose-built to automate clinical trial accruals, forecasting, budgeting, and benchmarking. To learn how leading biopharma finance teams are automating their R&D accruals with Condor, request a demo at condorsoftware.com.

Read more

AI
September 13, 2026

Introducing the World’s First Clinical Finance AI Agent Purpose-Built for Biopharma

Today we unveiled Condor's Clinical Finance AI Agent — the world's first AI agent purpose-built for biopharma R&D finance.

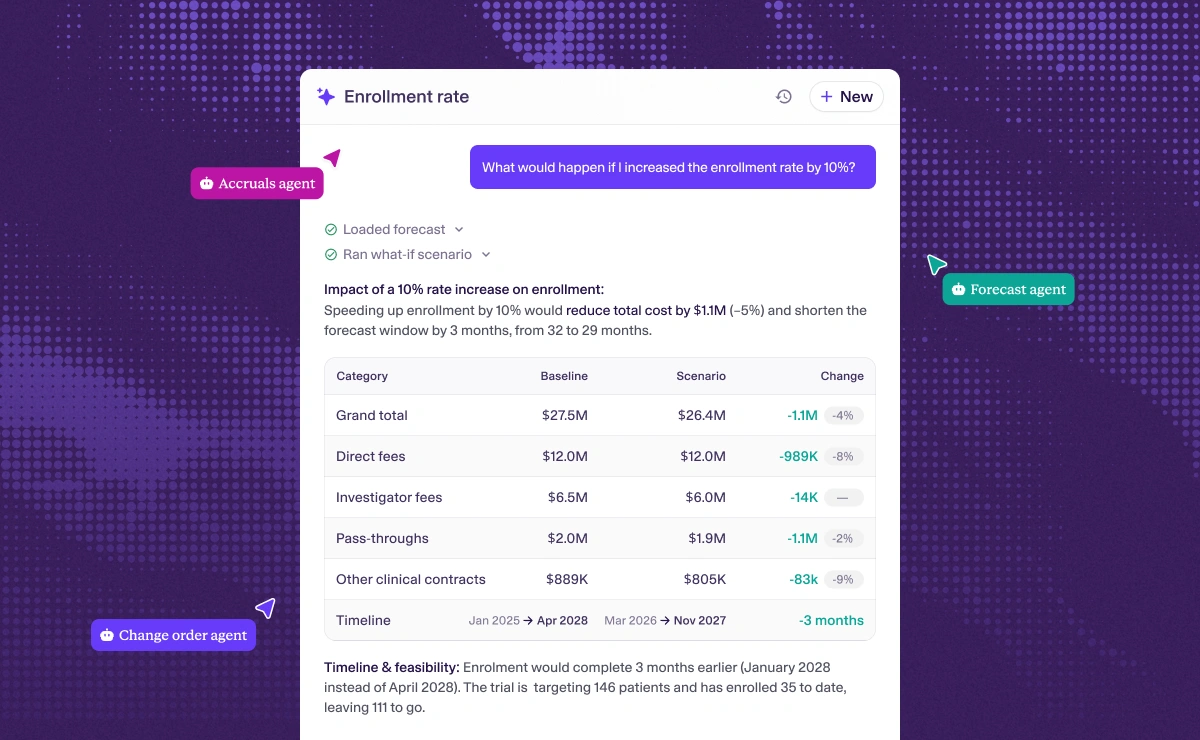
Ask it why a trial's actuals and forecast diverged, and it reasons across your full budget and forecast history to give you the answer in seconds, not the days it takes to reconcile across your ERP, CTMS, EDC, and a dozen spreadsheets. Ask it what a change in site mix or enrollment timing will cost you, and it runs the scenario and builds the resulting model directly in Condor. It doesn't just surface a number. It gives you the "why," and then it does the work.

This is a big milestone for our company and industry. It's also the moment I've been building toward since the day I started Condor.

The vision I had five years ago

When I founded Condor, I believed the financial machinery underneath every clinical trial could be fully automated, end-to-end, with AI reasoning on top of it. 

No more manually managing or outsourcing your finances. The numbers, built by an engine you can trust. Workflows run by AI. The why behind the numbers, uncovered in seconds instead of weeks, while there’s still time to act. 

Our new agent is the realization of that vision.

Why it took five years

Building AI that produces numbers you can actually trust is unbelievably hard. 

It took building Condor's financial engine first — a deterministic layer that follows defined rules, produces consistent output every time, and is fully auditable. No guessing, no black box, no "the model thinks it's probably right." Every number has to tie back to the clinical activity that actually drove it, because in this industry, a number nobody can defend is a number nobody will use.

It took building a knowledge graph grounded in a clinical and financial ontology we developed over years of work with Big 4 accounting firms — mapping how budgets, vendor contracts, clinical sites, and clinical activity actually connect to each other, across hundreds of studies and therapeutic areas. That ontology is what lets our agents understand a change order or a forecast variance the way a clinical finance team does, instead of the way a generic model guesses.

We built all of that first, five years ago, before there was a market pulling us to do it, because we knew it was the only foundation AI could stand on and still be trusted with a number that ends up in a board deck.

Recently, competitors that built their entire business model around outsourcing clinical finance — putting bodies behind the work instead of automating it — have realized AI is where our industry is headed. They're years behind, so the best they can offer is AI bolted on top of their services model. 

Layering AI onto a services model doesn't change what the AI is standing on. If the underlying data was never built for automation — if it was always meant to be assembled by a person — AI on top of it can move faster, but it can't reason with the same grounding as our AI platform. It will take those companies years to build what we have been building for the last five years, because an ontology and a knowledge graph like ours can't be retrofitted. They have to be the starting point.

Why our AI platform matters now, more than ever

For most of the last century, science was the bottleneck in drug development. AI is closing that gap fast, and pipelines are about to fill with more candidates than this industry has ever had to fund at once. Every one of those candidates still has to be forecasted, funded, and managed. Right now, the financial infrastructure doing that job is still, for almost everyone, a spreadsheet.

The bottleneck didn't disappear. It moved from the lab to the ledger. Today, Condor is the only platform built from the ground up to run biopharma R&D finance and operations at the scale AI-driven pipelines are about to demand. Because we built the engine, then the knowledge graph, then the agents, in that order, on purpose.

What comes next 

Our Clinical Finance Agent is one of a growing team of agents built on Condor's knowledge graph. Each one, including our forthcoming investigator grant agent, is purpose-built to remove a specific piece of manual work slowing R&D finance and clinical operations teams down.

My vision is here: No more manually managing your finances. The numbers built by our engine. The workflows run by AI. The why behind the numbers uncovered in seconds, not weeks, while there’s still time to act. 

This is the start of something big for our industry. 

If you want to see the agent for yourself, book a demo.

Read the article

AI
August 30, 2026

Reimagining Investigator Grants with AI

Here's what we keep hearing from clinical finance and ops teams: "I know we need to be doing something with AI. I just don't know how to start. Can you share practical, hands-on examples of how to use AI in clinical finance?" That question is why we kicked off our webinar series, Practical Applications of AI in Clinical Finance & Ops. It's built around one simple premise: real use cases, real workflows, real results. No theory, no hype, just what actually works.

Our first session tackled CRO change orders. Our latest webinar took on the biggest line item in almost every clinical budget: investigator grants.

Here's the webinar recording.

Why Focus on Investigator Grants?

Investigator grants aren't a line item you can afford to get wrong. On average, site payments for administrative fees and patient visits account for roughly 48% of total per-trial cost. The average investigator grant runs about $6,900 per patient across therapeutic areas, and oncology trials push that closer to $18,700 per completed patient. On a study of any real size, that's tens of thousands of individual transactions, each one needing to be verified against whether the activity actually happened and whether the invoiced amount matches what was contracted.

The people on the other end of those payments can't absorb your payment terms. Sites paid on a monthly cycle wait an average of 45 days to be reimbursed for work already performed. On quarterly terms, that stretches to 137 days, nearly three times the wait for the same work. Forty-three percent of sites report three months or less of operating capital in the bank, and CTTI estimates that 40% of site dropout is tied to payment delays. Twenty-three percent of sites report delays of 90 days or longer. Payment accuracy isn't a back-office hygiene issue. It's site relationship and enrollment risk.

Grants are also just structurally hard to get right. The activity and the money live in different systems: your EDC knows which visits happened, but finance typically only sees the invoice and payment files, with no line-by-line reconciliation between the two. Every site contract is its own snowflake of rates, invoiceable procedures, screen-fail caps, holdbacks, and overhead, all buried in contract PDFs that range from clean to, frankly, illegible. Protocols now average 3.3 substantial amendments, and each one can reprice visits and admin fees mid-study. And invoiceables like screen failures and unscheduled visits often accrue in the dark, surfacing all at once as a true-up at closeout instead of being tracked as they occur.

Most sponsors respond by outsourcing grants management to a CRO or payments vendor, and that's often the right call. CROs bring dedicated staff, global payment rails, and the ability to manage hundreds of site relationships at once so you don't have to build that function internally. But outsourcing the work isn't the same as outsourcing the accountability. Payments are frequently a low-margin, pass-through afterthought inside a much larger CRO contract, and you're trusting a vendor to approve, calculate, and report on its own work. When your auditors and your board have questions about the numbers, they're asking you, not your CRO.

We shared two stories from the field that show what happens when convenience wins out. In the first, a top-five global CRO replaced its investigator payments team with an automated pay platform that auto-paid every invoice it received. Sites started getting checks for patient visits that hadn't happened yet, and it took months to unwind the confusion. In the second, a mid-cap oncology sponsor closed out a trial and received a $5 million bill from its CRO for invoiceables that had never been tracked or accrued along the way. The money had already been spent; the sponsor was simply the last to find out. Automation without reconciliation just makes the wrong payment happen faster.

How to Reimagine Investigator Grants with AI

To show what's actually possible today, we ran the same investigator grant payment report through two very different tools: Microsoft Copilot, something most finance teams already have access to, and Condor's purpose-built platform.

Using Microsoft Copilot

Jeff started by dropping a CRO investigator grant payment file, covering the last two quarters of a phase 3 study, into Copilot with the following prompt:

I'm the head of clinical finance at a biotech company. Attached is the investigator grant payment report from our CRO for our phase 3 study covering the last two quarters. Please analyze it and give me: total payments by site and month, highlighting the five highest-paid sites; a breakdown of visit payments versus procedures versus invoiceable pass-through line items; any payments that look inconsistent with each site's contract budget or with the visits patients actually completed; what we should accrue for work sites have performed but not yet been paid for; and five questions I should ask the CRO before approving the next payment run. Format the output as a brief memo I can share with my CFO.

Two things make this prompt work. First, it's specific about exactly what the output should contain, since a general ask invites the model to fill gaps with something that merely looks credible. Second, it gives the model context on audience and intent, telling it who's asking and who the memo is for, so it knows what level of detail and framing to use.

Copilot came back with a clean executive summary: roughly $270,000 in payments, weighted toward startup activity and pass-through costs consistent with early enrollment, no obvious duplicate payments, but several items flagged for CRO follow-up. It broke out the top five paid sites, plotted payments by month, and split the mix between visits, procedures, and invoiceable pass-throughs. It flagged a 4-5 month lag between when sites performed visits and when they were reimbursed, and called out specific items, like a biopsy and imaging reimbursement paid before the associated screening visit, and ECG charges appearing months after their related visits.

For a tool that's already sitting in most people's Microsoft 365 license, that's a genuinely useful starting point: a fast, readable summary, clean per-site totals, catches on the obvious duplicates and outliers, and a CFO-ready memo in seconds with zero procurement.

But here's where it stops. Copilot can't see the EDC, so it can't tie a payment to a visit that actually happened. It doesn't know the contracted rates, caps, holdbacks, or overhead in the site agreements, so it has no way to know whether a flagged charge is actually wrong. The accrual figure it generates is an extrapolation of past payments, not a measurement of completed activity, and it can't distinguish an early payment from an unearned one. Run the same prompt twice and you may get a different answer, with no evidence trail behind either one. It reads the payment file. It cannot read the trial.

From "What the File Says" to "What's True": The Condor Demo

Nim then walked through the same investigator grant scenario inside Condor. Instead of reasoning from a single spreadsheet, Condor's Intelligence Engine reconciles patient-level activity, visits, procedures, and site admin fees coming from the CRO, directly against the EDC data sponsors already have, using AI to map each payment to the business context behind it. The system proposes the mapping automatically; nothing overrides a user's judgment without review, but the matching itself doesn't require anyone painstakingly reconciling line by line.

Once that file is imported, two things change. The overview surfaces CRO and site performance alongside payment reconciliation, flagging missing invoices and overbilling immediately and pointing to which sites need attention. And a trend layer goes beyond flagging individual discrepancies to surface patterns: what share of spend is startup versus investigative, which sites show unusual or no activity, and how performance is trending over time, the exact kind of history and pattern-matching a generic LLM has no way to see. From there, users can drill into the raw patient data, overlay it against processed EDC data in native currency or USD, and investigate a specific negative variance down to the site, visit, procedure, or admin fee level.

The platform is built around four core principles: the full story lives in one place instead of scattered across systems; overbilling, missing invoices, and pricing issues are visible at a glance instead of requiring a manual dig; discrepancies and off-contract charges are flagged as they appear; and everything is oriented toward decision support, so teams spend less time combing through data and more time acting on it.

Mapped back to the two stories from earlier in the session: the auto-pay trap becomes activity matching, every payment tied to a corresponding EDC event, so a payment with no visit behind it is caught before it goes out the door instead of after. And the closeout surprise becomes continuous invoiceables tracking, watching that spend accrue monthly as it happens, so it becomes a line item you tracked all along rather than a bill that shows up at the end.

What We Heard From the Room

Several attendees asked some version of, "If I upload my EDC and contract data into Copilot and structure the prompt correctly, can't I get there myself?" Short answer: to a point, yes, but volume becomes the constraint fast. Most general-purpose tools cap how many documents you can attach to a single prompt, well short of the dozens or hundreds of contracts a real trial generates. Without a knowledge graph or ontology behind it, there's no guarantee you get the same answer twice.

On data sources, Condor works from whatever level of detail a CRO provides, whether that's an accrual report or the underlying invoices, and the more detail available, the more granular the mapping. Unmapped invoiceables and procedures are clearly flagged in the reconciliation table so they can be reviewed and remapped rather than silently dropped. Protocol amendments are handled by loading the full history of a site's CTA, so a visit performed before an amendment's effective date is recognized at the old rate and everything after at the new one, even across sites with seven or eight amendments over a study's life. The platform supports full multi-currency and FX conversion, any therapeutic area, and, per attendees who asked directly, no cap on site count. Some phase 3 oncology trials on the platform run 500-plus sites, each with its own contract history, and international sites are handled the same way as domestic ones, loaded through automation and human-in-the-loop review into the same normalized EDC and contract structure.

What's Next in the Series

This is only our second session, and we've already received multiple topic ideas from attendees. Our next webinar will be in early October, and we’ll share the topic soon. 

In the meantime, if you'd like to see what Condor can automate for your investigator grants process specifically, book a demo with our team here.

Read the article

AI
July 26, 2026

Reimagining CRO Change Order Management with AI

Here’s what we keep hearing from clinical finance and ops teams:

"I know we need to be doing something with AI. I just don't know how to start. Can you share practical, hands-on examples of how to use AI in clinical finance?"

The answer is yes, absolutely. To help, we’ve kicked off a series we call Practical Application of AI in Clinical Finance & Ops. It’s built around one simple premise: real use cases, real workflows, real results. No theory or hype. Just what actually works.

Our first webinar focused on the three levels of AI maturity, the AI mindset teams must have to successfully implement and scale AI, and how AI is evolving and what that means for pharma clinical finance and ops teams. 

Our latest webinar focused on reimagining CRO changes order management with AI. 

Why Focus on CRO Change Orders?

If you work in clinical finance or clinical operations, you don't need convincing on this one. Change orders are one of the most painful, recurring problems, and the data backs up what everyone already feels. Substantial protocol amendments, which are the main trigger for change orders, have gone from affecting 57% of trials a decade ago to 76% today. In Phase 3, it's 82%. On average, a Phase 3 change order runs $535,000, which is close to four times the Phase 2 figure, and takes about three months to negotiate.

Scale that across a typical portfolio, say eight active studies, and you're looking at 40 to 50 change orders across the portfolio, including ancillary vendors. That represents $10 million or more in unplanned, unbudgeted costs. Meanwhile, change order volume has roughly doubled over the past decade, while finance headcount at a typical biotech has stayed flat. That gap gets closed one of three ways: with tooling, headcount, or with weekends.

On top of the volume problem, change orders are just hard to review. The explanations on each line item are often a sentence or two. CROs sometimes lowball the initial bid, knowing the change order process is where they recover margin. And retrospective work, cost for activity that already happened, routinely shows up buried in a document you're given a week or two to evaluate. It's a lot of financial exposure moving through a process with very little tooling behind it. That combination of high stakes and low tooling made it the obvious place to start.

How to Reimagine Change Order Management with AI

In the webinar, we walked through the same change order budget three different ways: first with generic AI, Microsoft Copilot. Then with Condor's purpose-built AI, Talon. And finally by flipping the process entirely and modeling the scope change in Condor before the CRO's document even arrives.

Using Microsoft Copilot

One of the most common requests after the panel was for something people could go use immediately. If you have Microsoft 365, you already have Copilot, and that's genuinely a useful starting point for a first pass at any change order. Here's the exact prompt we used in the webinar:

"I'm a finance director at a biotech company. I've received the attached change order budget from a CRO for a Phase 3 study. Please analyze it and give me a summary of the total cost change and the top five largest cost increases, a breakdown of direct fees versus pass-through costs versus investigator costs, any line items that appear to be retroactive or cover work already performed, and a list of five questions I should ask the CRO before approving this change order. Format the output as a brief memo I can share with my CFO."

A few things worth noting about why this prompt works: it gives the model a role ("I'm a finance director"), a specific task, and a defined list of deliverables. The more context you give a general-purpose model before you hit send, the better the output. Attach your change order file, run this, and in under a minute you'll have a readable first-pass memo.

Just know where it stops. A general-purpose tool can tell you what a document says. It can't tie units back to your original contract, it has no knowledge of your protocol history, and it won't reliably catch unlabeled retroactive work. It gets you from zero to informed. It doesn't get you to defensible. That's the gap purpose-built, ontology-driven tools like Talon are built to close, and it's why the answers looked meaningfully different once we ran the same budget through a model that actually understood the contract underneath it.

From "What Changed" to "What's Wrong": The Talon Demo

That's the gap we closed with the next demo. I ran the exact same change order budget through Talon, an AI-powered service offering we’re rolling out to customers, which has our clinical and financial ontology built into it. Instead of just summarizing what changed, Talon made judgment calls on every line item: it flagged that roughly 94% of the total dollar delta was unjustified, inadequately supported, or needed clarification, and sorted every line into a clear disposition, hard no, negotiate, needs clarification, or accept. It landed on a negotiation target of $1.4 to $1.7 million in recoverable savings, with a realistic settlement range of $556,000 to $856,000 given how CROs typically respond to pushback.

The reasoning behind that is what makes it useful. On the largest cost driver in the change order, added monitoring visits, Talon explained that monitoring spend is mechanically tied to patient volume, not site count, and since patient counts hadn't changed, the increase didn't hold up. It reverse-engineered the expected cost from the original contract's drivers (per-patient procedures, per-site fees) and showed the gap between that and what the CRO was billing, with every finding linked back to the source cell in the change order budget grid. Microsoft Copilot told us what the document said. Talon told us what it was hiding, and gave us a negotiation brief to send back to the CRO.

Getting Ahead of the Change Order Entirely: The Condor Scenario Planning Demo

The last demo flipped the sequence altogether. Instead of waiting for a CRO's change order and then analyzing it, I modeled the scope change myself, before any document arrived, directly in Condor's production environment. I typed a plain-language prompt asking the system to forecast a scenario for the study: expand from seven to 11 sites, keep the 48-month duration and hold patient counts flat, then show the incremental cost against the current $10.67 million contract value.

Condor's forecasting agent built that scenario in real time, referencing the study's actual contract structure and cost drivers, and landed on a $629,000 incremental increase. Compare that to the $2 million-plus the CRO's change order was requesting for the same scope, and the gap tells you everything: once you strip out costs that shouldn't move when patient volume doesn't (like a big chunk of that monitoring spend), the real cost of the change is a fraction of what was billed. That's the value of scenario planning: you walk into the negotiation with your own independent number already in hand, instead of reacting to whatever number the CRO sends first.

Here’s the webinar recording.

We’ve trimmed the Talon and Condor demos from it. Want to see all the demos, and see what this looks like with your own data? Book a demo with our team here.

What's Next in the Series

As I mentioned, this is the second of several webinars and workshops in our Practical Applications of AI in Clinical Finance & Ops series. We polled attendees live during the webinar on what they wanted to see next, and the results were clear. Here are a few of the topics we’ll cover:

  • Monitoring vendor spend pacing against contract value and identifying anomalies in vendor invoices (the top pick)
  • Building a first trial budget from a protocol
  • Building an AI prompt library for your clinical finance team

We'll be running these both as webinars and as in-person live workshops at upcoming industry events, where you can bring your laptop and work through the exercises with us in real time. Stay tuned for updates!

Read the article